Beyond LDL cholesterol: why ApoB and lipoprotein(a) could save your life
ApoB and Lipoprotein(a) testing reveals hidden heart disease risks that standard cholesterol tests often miss, providing a clearer picture of cardiovascular health.

On this page
In short
- ApoB and lipoprotein(a) add cardiovascular risk information an LDL result can miss, as ApoB estimates particle number and Lp(a) often reflects inherited risk.
- ApoB can be raised while LDL cholesterol looks acceptable, a mismatch that can occur with high triglycerides, diabetes or metabolic syndrome.
- Lp(a) is largely inherited and changes little with diet, so it is often measured once, and your GP still works on other risk factors.
From Vively member data
ApoB and lipoprotein(a) results add information about cardiovascular risk that an LDL cholesterol result can miss. Higher ApoB suggests more atherogenic particles, while high lipoprotein(a) often reflects inherited risk. Neither result predicts an individual heart attack. Your GP interprets them alongside cholesterol, blood pressure, diabetes, smoking and your personal and family history.
Our ApoB test page explains the marker and testing details. This article focuses on what ApoB and lipoprotein(a), also called Lp(a), can mean for your next conversation with your GP.
What ApoB adds to LDL cholesterol
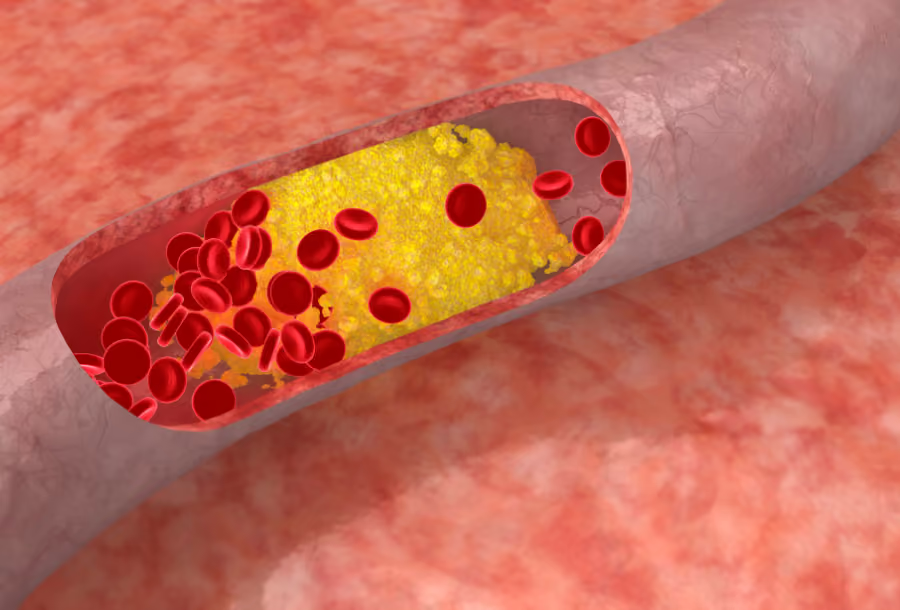
ApoB is a protein carried on lipoprotein particles that can contribute to plaque in artery walls. Its concentration provides an estimate of the number of atherogenic particles, meaning particles involved in atherosclerosis.
LDL cholesterol describes the cholesterol carried inside LDL particles. ApoB describes particle burden. These measurements often move together, but sometimes the cholesterol load and the number of particles tell different stories.
For example, LDL cholesterol can appear acceptable while ApoB is raised. This mismatch, called discordance, can occur with high triglycerides, diabetes or metabolic syndrome. The American Heart Association notes that ApoB can add useful information in these circumstances.
ApoB testing measures a protein concentration rather than directly counting particles under a microscope. It adds to a standard lipid profile; it does not make LDL cholesterol or the rest of a cardiovascular assessment irrelevant.
Some practitioners also order LDL subfraction testing, which estimates LDL particle size, or oxidised LDL. Our page on LDL subfractions and LIPOSCREEN explains what these tests add and where the evidence is limited.
What lipoprotein(a) adds to your risk assessment
Lp(a) is an LDL-like particle with an additional protein called apolipoprotein(a). Higher levels are associated with cardiovascular disease and narrowing of the aortic valve. Levels are largely inherited, so high Lp(a) can occur in someone who eats well and is physically active.
A normal LDL cholesterol result does not rule out high Lp(a). A standard lipid panel does not usually include it. Personal or family history of early cardiovascular disease, known high Lp(a) in the family, or familial hypercholesterolaemia are reasons to discuss testing with your GP.
High Lp(a) usually has no symptoms. The result describes a risk factor, not proof that an artery is blocked. Other risk factors still influence what the result means for you.
How to read an ApoB or Lp(a) result
Check the test name, unit and laboratory interval before comparing your number with an online chart. ApoB and Lp(a) use different units and cannot be interpreted as the same measurement.
ApoB reference ranges and treatment targets differ
Vively’s approved ApoB general reference range is 0.48 to 1.3 g/L. The Vively optimal value is below 0.8 g/L. These describe our published marker ranges, not a universal treatment threshold.
Your GP may set a different target if you already have cardiovascular disease or a higher clinical risk. A result inside a general laboratory range does not settle whether further risk reduction is needed.
Lp(a) units need particular care
Vively’s approved Lp(a) reference upper limit is 100 nmol/L, with an optimal value below 75 nmol/L. These are Vively’s published ranges rather than a guarantee of safety below a particular number. Risk is continuous and depends on the wider clinical picture.
Some laboratories report Lp(a) in mass units, such as mg/dL, and others in molar units, such as nmol/L. There is no reliable fixed conversion for an individual result because particle size varies. Compare reports using the original units and ask your clinician or laboratory if the methods differ.
What high results can mean together
ApoB and Lp(a) can be raised separately or together. The response depends on which result is abnormal and the rest of your health profile.
- Raised ApoB with less striking LDL cholesterol: may identify a higher particle burden than the LDL result alone suggests. Review triglycerides, diabetes risk and other clinical factors.
- Raised Lp(a) with otherwise reassuring lipids: can indicate inherited risk that deserves attention even when routine cholesterol results look acceptable.
- Both markers raised: gives your GP more reason to assess the full risk pattern and discuss a plan. The numbers do not establish whether plaque is already present.
- Results within range: do not rule out cardiovascular disease or cancel risk from smoking, high blood pressure, diabetes or a strong family history.
Your GP may also consider kidney or thyroid disease when interpreting an unexpected result. Our article on thyroid test patterns explains that separate assessment.
What you can change when Lp(a) is inherited
A heart-healthy lifestyle can reduce cardiovascular risk even when it does not meaningfully lower Lp(a). High Lp(a) is not evidence that you have failed to eat or exercise well.
Work with your GP on LDL cholesterol, blood pressure, diabetes management and smoking cessation where relevant. The Australian Atherosclerosis Society’s patient information emphasises managing these other factors when Lp(a) is raised.
A practical eating pattern includes vegetables, fruit, legumes, whole grains, nuts and appropriate protein sources. Replacing some saturated fat with unsaturated fats can support cholesterol management. Regular activity and sustainable weight management, where appropriate, also support cardiovascular health.
These measures may improve ApoB and other risk factors, but the effect varies. Do not use a small dietary study or a supplement claim as a promise that Lp(a) will fall. Prescription treatment decisions belong with your treating doctor.
Follow-up testing depends on the marker
ApoB can help monitor response to a clinical management plan. Your GP decides when a repeat result will be useful, based on any treatment changes and your risk profile.
Lp(a) is often measured once because levels are largely genetically determined and relatively stable. Repeat testing may be appropriate in selected circumstances. If your result is raised, ask whether close relatives should discuss testing with their own doctors.
A glucose sensor cannot measure ApoB, Lp(a) or arterial plaque. A change in glucose readings cannot demonstrate that these lipid markers have improved.
How Vively can help you understand your results
We help you review blood results together and discuss nutrition and lifestyle with a practitioner. Our lipoprotein(a) test page covers the related marker. The Baseline Health Check provides broader general health context, while your GP manages cardiovascular diagnosis and treatment.
For access, current costs and preparation, use the linked test pages. ApoB and Lp(a) are not part of the Baseline. Vively members can add them through the Longevity Panel ($199: ApoB, ApoA1, Lp(a) and homocysteine), and they are also in the Full Body Health Check ($300). Your test referral is issued straight away when you order, and a doctor in our network signs off every request, so you don't need a referral from your own GP.
Frequently asked questions
Can ApoB be high if LDL cholesterol is in range?
Yes. The cholesterol carried inside particles and the number of particles do not always match. ApoB can add information when triglycerides are high or someone has diabetes or metabolic syndrome. Your GP considers both results alongside other risk factors rather than choosing one marker to explain your entire risk.
Will changing my diet lower Lp(a)?
Lp(a) is largely inherited and usually changes little with diet or exercise. Healthy habits still matter because they can improve other cardiovascular risk factors. Work with your GP on cholesterol, blood pressure, diabetes and smoking where relevant, rather than judging progress only by whether the Lp(a) number falls.
Does a high result mean I am having a heart attack?
No. ApoB and Lp(a) are risk markers and do not diagnose an acute heart attack. New chest pain or pressure, severe breathlessness, fainting or other possible heart attack symptoms need emergency assessment regardless of previous blood results. Do not wait for a routine appointment or another lipid test.
Sources
- American Heart Association: ApoB and cardiovascular risk.
- American Heart Association: lipoprotein(a).
- HEART UK: high lipoprotein(a), units and follow-up.
- Australian Atherosclerosis Society and FH Australasia: lipoprotein(a) patient information.
- RCPA Manual: apolipoprotein B.
- HEART UK consensus statement: Lp(a) measurement and conversion limits.
- Heart Foundation: heart-healthy eating pattern.
The Baseline Health Check is a blood test covering 70+ markers at one of 3,700+ collection centres. Your dietitian goes through your results with you and builds your plan. $99$79 this Black Friday, ends 1 Dec. Then $99 a month, cancel anytime.