What is the anion gap?
The anion gap is the difference between the main positively charged electrolytes in your blood (sodium and potassium) and the main negatively charged ones (chloride and bicarbonate). Your blood always carries balanced charge, so the "gap" stands for the negative particles labs don't routinely measure: mostly the protein albumin, plus phosphate, sulfate and small acids such as lactate.
It is worked out like this:
Anion gap = (sodium + potassium) minus (chloride + bicarbonate)
For example, a sodium of 140, potassium of 4, chloride of 104 and bicarbonate of 26 mmol/L gives 144 minus 130, which is an anion gap of 14 mmol/L.
Some labs leave potassium out of the calculation. That gives a result about 4 mmol/L lower, so their reference range is lower too. This is one reason anion gap ranges vary more between labs than most markers.
What does an anion gap blood test show?
The anion gap helps a doctor work out why the blood has become too acidic, by sorting the cause into one of two groups. When bicarbonate is low:
- A high anion gap suggests an extra acid has been added to the blood, such as ketones, lactate or waste acids that failing kidneys can't clear.
- A normal anion gap suggests bicarbonate is being lost, usually through the bowel or kidneys, and chloride has risen to fill the space.
Because it is calculated, the anion gap carries the small measurement variation of all four electrolytes added together. A difference of 2 or 3 mmol/L between tests can be nothing more than that. If your bicarbonate is normal and you feel well, a slightly unusual anion gap rarely points to a problem. It matters when it sits with a low bicarbonate, abnormal kidney markers or symptoms.
Anion gap normal range
Using sodium, potassium, chloride and bicarbonate, a typical adult range is about 8 to 16 mmol/L, but ranges vary between labs.
| Range |
|---|
| Typical lab reference range (adults) | 8 to 16 mmol/L |
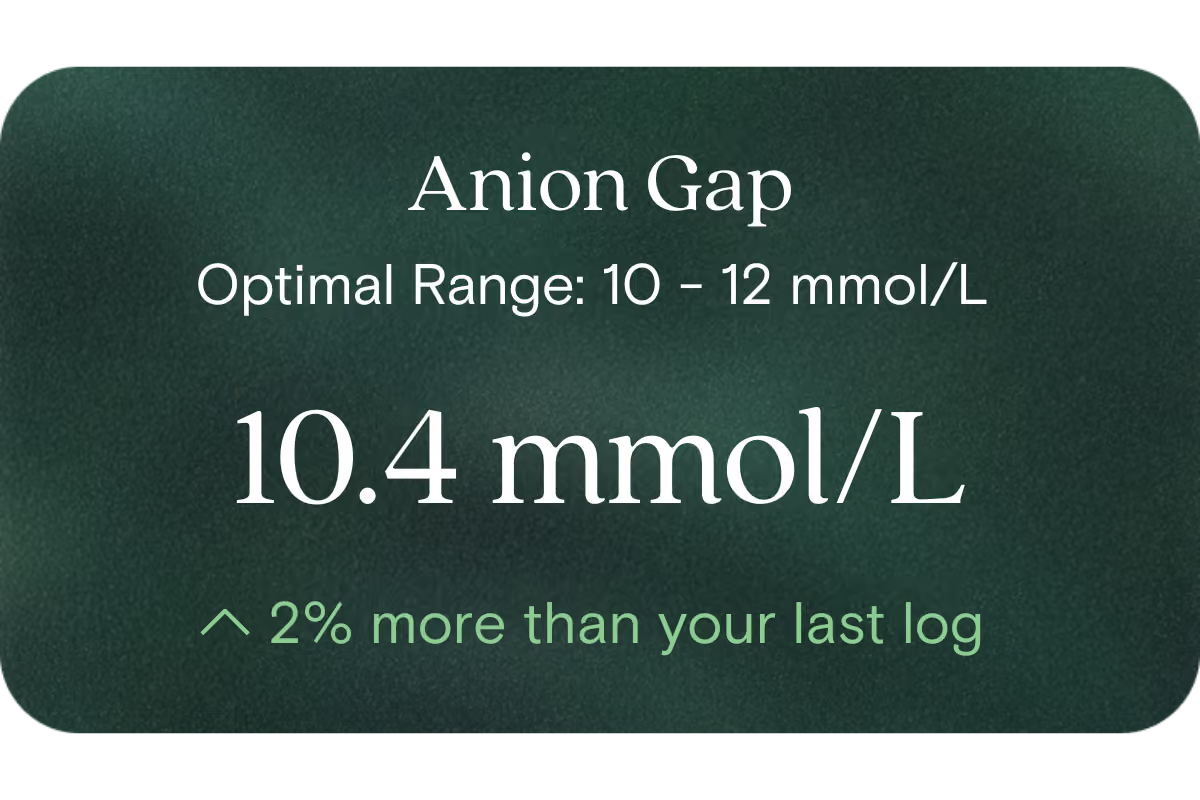
| Vively optimal range | 10 to 14 mmol/L |
Always read your result against the range printed on your report. Our optimal range is a soft guide for long-term health, not a diagnostic cut-off, and for a calculated marker like this one, your bicarbonate and kidney results matter more than where the gap sits.
What does high anion gap mean?
A mildly high anion gap with a normal bicarbonate, in someone who feels well, is most often lab variation or mild dehydration and rarely needs action. A high anion gap with a low bicarbonate means an acid may be building up, and that needs a doctor, urgently if you're unwell.
Common, everyday reasons for a mildly high result:
- Lab variation. Small differences in four measurements add up in the calculation.
- Dehydration. Concentrating the blood raises albumin, which nudges the gap up.
- A long fast or very low carb eating. Ketones add a small amount of acid.
- Very hard exercise shortly before your test, which produces lactate for a short time.
- A sample that waited before testing. Bicarbonate falls and potassium can rise as blood sits, which both push the calculated gap up.
Medical causes, which usually come with a low bicarbonate:
- Reduced kidney function, where acids the kidneys normally clear build up. Creatinine and eGFR will usually be abnormal too.
- Diabetic ketoacidosis, usually with high glucose. This is a medical emergency.
- Lactic acidosis from serious illness such as severe infection.
- Alcohol-related ketoacidosis, after heavy drinking with little food.
- Poisoning, for example with methanol, antifreeze or a large aspirin overdose.
What does low anion gap mean?
A low anion gap is uncommon, and most often reflects lab variation or a low albumin. It does not cause symptoms.
- Low albumin. Albumin is the biggest unmeasured negative particle in blood, so when it falls, the gap shrinks. For every 10 g/L that albumin drops, the anion gap falls by about 2.5 mmol/L.
- Lab variation, as with a mildly high result.
- Rarely, high levels of abnormal antibodies (paraproteins), as in multiple myeloma, which often show up as a high globulin, or high blood levels of lithium, a medicine used for mood disorders.
What can affect your anion gap result
Anything that changes sodium, potassium, chloride, bicarbonate or albumin will change your anion gap.
- Do you need to fast? Not for the anion gap itself. An overnight fast for your Baseline's glucose and insulin is fine; going a day or more without food can raise the gap slightly through ketones.
- Hydration. Keep drinking water as usual.
- Hard exercise. A big session shortly before your draw adds lactate, so train afterwards instead.
- Medicines. SGLT2 inhibitor diabetes medicines can raise ketones, and lithium can lower the gap. Mention either to your practitioner.
How the anion gap fits with your other results
The anion gap only makes sense next to the numbers it's built from, and a trend across several tests tells you more than one result.
| Pattern | What it can mean |
|---|
| Slightly high or low anion gap, normal electrolytes and albumin, you feel well | Usually lab variation. No action needed; we'll look again on your next test. |
| High anion gap with low bicarbonate | The classic sign of an added acid. Your glucose and kidney results help show which one. Needs GP review, urgently if you're unwell. |
| High anion gap with high creatinine and low eGFR | Points to acids the kidneys would normally excrete, such as phosphate and sulfate. Needs GP review. |
| Normal anion gap, low bicarbonate, high chloride | No added acid. This is the bicarbonate-loss pattern seen with ongoing diarrhoea or kidney tubule problems. Needs GP review. |
| Low anion gap with low albumin | An expected effect of low albumin. The albumin result needs looking at. |
How to support healthy anion gap levels
Lifestyle supports a healthy anion gap indirectly, by keeping its building blocks steady and protecting your kidneys and metabolic health.
- Keep blood glucose in check. If you have diabetes, know the warning signs of ketoacidosis, especially if you take an SGLT2 inhibitor. Our fasting glucose page explains the numbers.
- Build meals around vegetables, legumes and wholegrains, and have meat and cheese alongside them. This lowers the acid load your kidneys clear each day, which matters most if your kidney function is reduced.
- Avoid heavy drinking, especially without eating, which can trigger alcohol-related ketoacidosis.
- Look after your kidneys by keeping blood pressure in range and limiting regular anti-inflammatory painkillers.
When to see your GP
See your GP if your anion gap is high and your bicarbonate is low, if the gap is outside your lab's range on a repeat test (for example 18 mmol/L or above, or 4 mmol/L or below), or if it sits with abnormal kidney markers or a low albumin. A very high anion gap, above about 25 mmol/L, needs prompt medical attention.
Seek urgent care for fast or deep breathing, ongoing vomiting, abdominal pain, confusion or extreme drowsiness, especially if you have diabetes or have been drinking heavily. If you think someone has swallowed something toxic, call 000 or the Poisons Information Centre on 13 11 26.
Testing anion gap with Vively
Your anion gap is calculated from the sodium, potassium, chloride and bicarbonate measured in Vively's Baseline Health Check, and read with your albumin, creatinine and eGFR. The referring doctor reviews each Baseline request, which can change the exact markers included.
Once you've signed up online, our GP network sends through your referral. You visit one of 4,000+ accredited partner collection centres for a single blood draw, and results come through in the app usually within a few days, set against optimal ranges with plain-English explanations. A practitioner then talks you through them and shapes a personalised plan, and later retests show which way your markers are heading. If your anion gap is a touch out and everything else is fine, we'll tell you that.
See your anion gap in context with the Baseline Health Check.
Frequently asked questions
Do I need to fast before an anion gap test?
No. The standard overnight fast for your Vively Baseline, which covers glucose and insulin, has no meaningful effect on the anion gap. Fasting much longer can, because ketones are acids that widen the gap a little. Keep to an overnight fast and drink water as usual beforehand.
Is an anion gap of 17 high?
Yes, slightly. It is one point above a typical upper limit of 16 mmol/L, though labs that include potassium often use higher ranges. With a normal bicarbonate and kidney markers, and no symptoms, it is most likely lab variation or mild dehydration. If your bicarbonate is low too, see your GP.
Should I worry about a slightly low anion gap?
Usually not. A slightly low anion gap with normal albumin and globulin is most often lab variation. If your albumin is low, that explains the low gap, and the albumin result is the one worth discussing with your practitioner or GP.
Why is my lab's anion gap range different?
Because labs calculate it in slightly different ways. Some include potassium and some leave it out, which shifts results by about 4 mmol/L, and different analysers add their own small differences. The range printed on your own report is the one to compare your result with.
Can I get an anion gap test through Medicare?
Yes, indirectly. The anion gap is calculated from your electrolytes, and many blood tests like these can be Medicare-funded when a doctor orders them for a clinical reason. Through Vively, our GP network arranges the referral as part of your Baseline Health Check, and the gap is calculated from those results.
Does Vively replace my GP?
No. We help you understand and act on your results, and with a calculated marker like the anion gap, we'll flag when a pattern needs a doctor's eyes. You should still see your GP for diagnosis, treatment, prescriptions, urgent symptoms and any ongoing medical conditions.
References
- Royal College of Pathologists of Australasia (RCPA). RCPA Manual: Anion gap.
- Pathology Tests Explained. Electrolytes. https://www.pathologytestsexplained.org.au
- Kraut JA, Madias NE. Serum anion gap: its uses and limitations in clinical medicine. Clinical Journal of the American Society of Nephrology. 2007;2(1):162-174.
- Figge J, Jabor A, Kazda A, Fencl V. Anion gap and hypoalbuminemia. Critical Care Medicine. 1998;26(11):1807-1810.
- Pandey DG, Sharma S. Biochemistry, Anion Gap. StatPearls. NCBI Bookshelf.
- Merck Manual Professional Version. Metabolic acidosis. https://www.merckmanuals.com/professional/metabolic-and-endocrine-disorders/acid-base-regulation-and-disorders/metabolic-acidosis